

By Birth & Baby University · Last updated: October 2026 · 3 min read
People rarely use a single approach in labor. Many start with movement and water, add a medication later and still need comfort afterward. Yet research often compares one approach with another, not combinations. This article reviews what the reviews say, what they cannot tell us, and how doulas can honor every preference.
Key takeaways
- Cochrane classified epidural, combined spinal epidural and inhaled analgesia as effective for pain but with adverse effects, and several non-drug methods as “may work” with few adverse effects.
- Continuous one-to-one support was associated with less intrapartum analgesia and less regional analgesia use, and with fewer cesareans, in low-quality evidence.
- Non-drug approaches used as part of hospital strategies were associated with benefits without additional harm in a 2014 meta-analysis, but the studies mostly compared methods with usual care, not with combinations.
- No source reviewed here shows that one preference leads to better outcomes than another for an individual.
What the research says
A map of options
The Cochrane overview of 15 Cochrane reviews (255 trials) and three non-Cochrane reviews (55 trials) sorted interventions into categories. “What works” included epidural, combined spinal epidural and inhaled analgesia, all of which effectively manage pain but may cause adverse effects. Epidural was associated with more instrumental births, hypotension, motor blockade, fever and urinary retention, with no difference in cesarean overall. “What may work” included immersion, relaxation, acupuncture, massage and some nerve blocks. “Insufficient evidence” included hypnosis, sterile water injection, TENS and aromatherapy. The overview noted that most non-pharmacological methods appear safe but their efficacy is unclear, and that direct comparisons between different interventions were few.
Epidural versus other options
The Cochrane review of epidural analgesia found epidurals gave lower pain scores and higher satisfaction with pain relief than opioids, with more assisted vaginal births overall but not after 2005, and no difference in cesarean. This is a comparison with other analgesia, not with combinations of epidural and non-drug measures.
Continuous support
The Cochrane review of continuous support (26 trials, 15,858 women) found that those with continuous one-to-one support were less likely to use any intrapartum analgesia (RR 0.90, 95% CI 0.84 to 0.96) or regional analgesia (RR 0.93, 95% CI 0.88 to 0.99), and less likely to have a cesarean (RR 0.75, 95% CI 0.64 to 0.88, low-quality evidence). Subgroup analyses suggested the largest cesarean reduction when the provider was in a doula role and in settings where epidural was not routinely available. The pooled estimates are not a doula-only effect, many trials took place where policies on companions differed from today, and no trials were from low-income settings.
Non-drug approaches as part of hospital strategies
A 2014 meta-analysis grouped non-drug approaches by mechanism and found that approaches based on gate control and diffuse noxious inhibitory control were associated with fewer epidurals and higher satisfaction. Compared with approaches based on education, attention deviation and support, usual care was associated with higher odds of epidural, cesarean, instrumental birth and oxytocin use and lower satisfaction. The authors concluded that non-drug approaches used as part of hospital pain-relief strategies provide benefits without additional harm, and that tailored approaches based on continuous support were most effective for reducing interventions.

What this means for doulas
- Do not rank choices. The evidence does not show that choosing medication is a worse or better choice for an individual. Support the person’s decision.
- Describe tradeoffs, not virtue. Medicated and non-medicated options have different benefits and side effects.
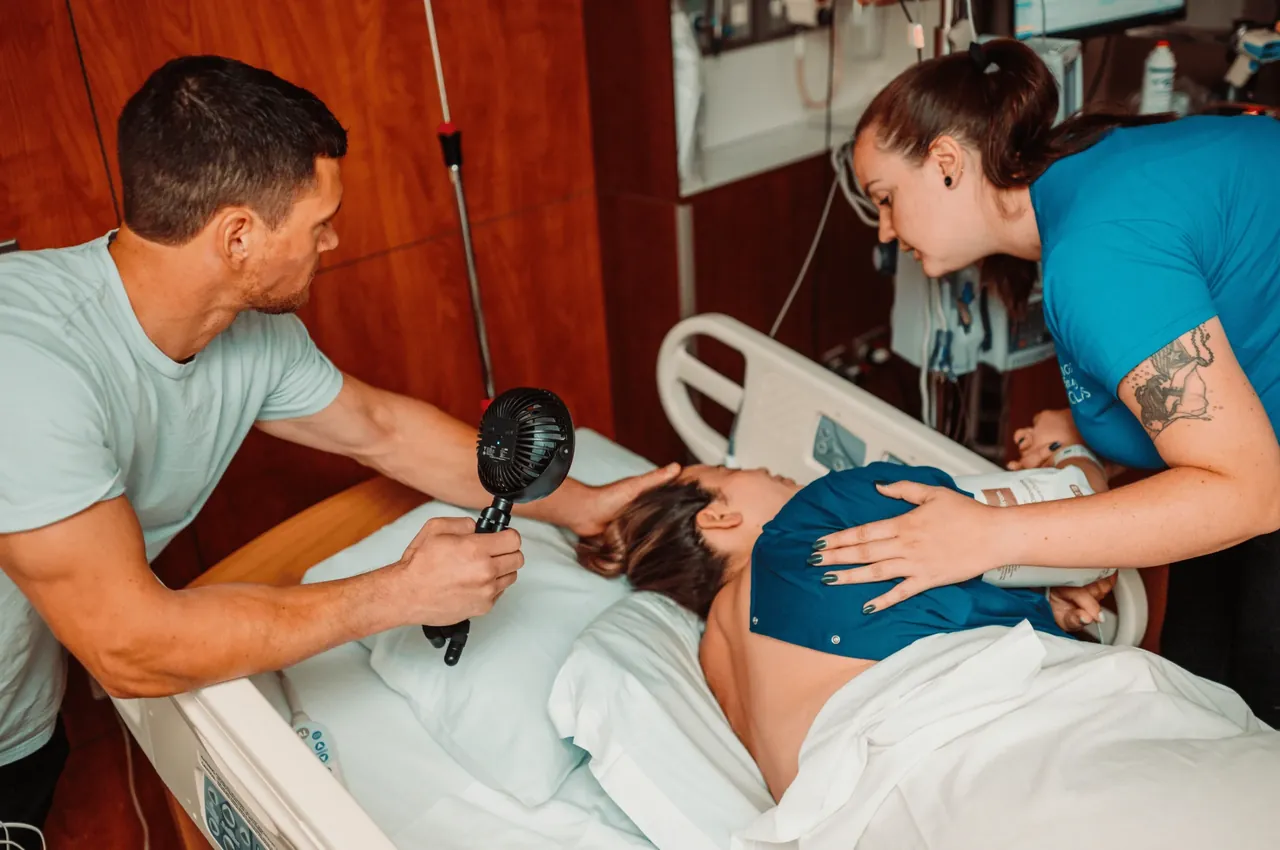
- Use non-drug support at every stage. Comfort, reassurance, position changes and presence remain useful with or without medication. Evidence for support is stronger than for any single technique.
- Explain, do not decide. Medication questions go to the anesthesia and obstetric team.
Putting the evidence into practice
- Create a flexible prenatal plan that lists comfort tools and medical options, with the client’s feelings about each, and revisit it as labor changes.
- Ask what the person wants you to do if they choose an epidural, and agree that your role continues.
- Use language like “the next step in your plan” instead of “giving in” or “holding out.”
- After birth, affirm decisions and avoid judging outcomes against the plan.
The bottom line
Pain relief in labor is a set of tools, not a ladder. The evidence supports continuous support, honest information and respect for each person’s choices, while leaving open how best to combine methods. Doulas help most by being present for every version of a birth.
This article is for professional education. It is not medical, legal or tax advice. Check the standards of your certifying organization and the rules where you work.
Sources and further reading
- Jones L, et al. Pain management for women in labour: an overview of systematic reviews. Cochrane Database of Systematic Reviews 2012. Read the source
- Anim-Somuah M, et al. Epidural versus non-epidural or no analgesia for pain management in labour. Cochrane Database of Systematic Reviews 2018. Read the source
- Bohren MA, et al. Continuous support for women during childbirth. Cochrane Database of Systematic Reviews 2017. Read the source
- Chaillet N, et al. Nonpharmacologic approaches for pain management during labor compared with usual care: a meta-analysis. Birth 2014. Read the source
Supporting every birth preference is central to doula practice. See the doula training and mentorship options on the For Doulas page.
More for professionals: the Professionals Blog.



Leave a Reply