
By Birth & Baby University · Last updated: October 2026 · 4 min read
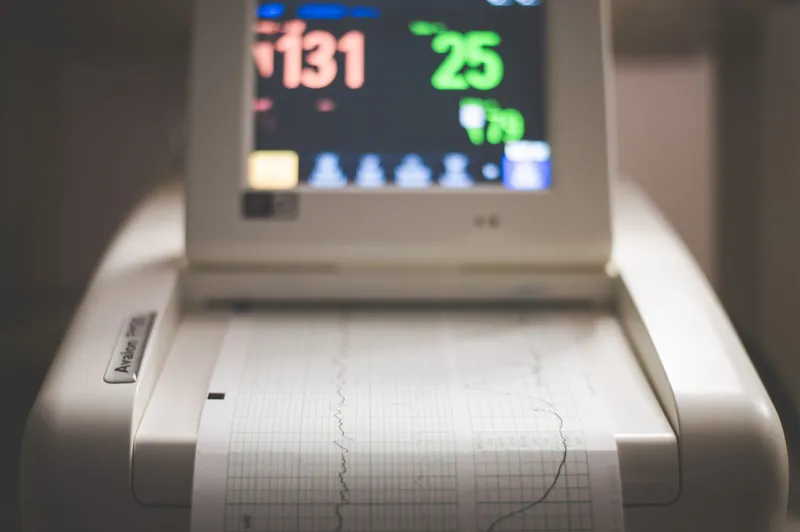
The fetal monitor is the most visible piece of equipment in many labor rooms, and the one doulas are most often asked about. Families notice the sound, the lines on the screen and the way nurses glance at it. This article explains the basics at the level of a nonclinical birth worker: what the research and guidelines say, where the limits are and what you can appropriately do. It is not training in reading tracings, and doulas should not interpret them.
Key takeaways
- Electronic fetal monitoring records the fetal heart rate and contractions. Interpreting the tracing is a clinical skill that belongs to the licensed team.
- A Cochrane review of 13 trials with over 37,000 women found continuous monitoring was associated with about half the rate of neonatal seizures but more cesarean and instrumental births, with no clear difference in cerebral palsy or perinatal death.
- ACOG’s 2025 Clinical Practice Guideline No. 10 describes a three-tier category system and recommends routine care for category I tracings and specific responses to category II and III tracings.
- A systematic review of 49 studies found interpretation agreement is variable, so clinicians themselves may read the same tracing differently.
What the research says
Continuous monitoring versus intermittent listening
The 2017 Cochrane review of continuous cardiotocography included 13 trials with over 37,000 women. Compared with intermittent auscultation, continuous monitoring showed no significant improvement in overall perinatal death (RR 0.86, 95% CI 0.59 to 1.23) and no difference in cerebral palsy (RR 1.75, 95% CI 0.84 to 3.63), but neonatal seizures were halved (RR 0.50, 95% CI 0.31 to 0.80, moderate-quality evidence). Cesarean birth rose (RR 1.63, 95% CI 1.29 to 2.07) and so did instrumental vaginal birth (RR 1.15, 95% CI 1.01 to 1.33), both low-quality evidence. The authors noted that the challenge is conveying these results to women so they can make an informed decision without compromising the normality of labor, and that the long-term meaning of reduced neonatal seizures is unclear. Most trials were at high risk of performance bias.
ACOG’s Committee Opinion 766 summary says continuous electronic monitoring has not been shown to significantly affect outcomes such as perinatal death and cerebral palsy in low-risk pregnancies. Whether a particular person is offered intermittent listening is a clinical and local-policy question, based on risk.
How tracings are categorized
The 2008 NICHD workshop report described a three-tier system for interpretation. ACOG’s Clinical Practice Guideline No. 10 (October 2025) provides an evidence-based framework for evaluating and managing intrapartum heart rate patterns. In a published summary of its recommendations, ACOG recommends routine intrapartum care for category I tracings, initial attempts at intrauterine resuscitation (for example position changes, a maternal fluid bolus, or reducing or stopping augmentation agents) before cesarean birth for a category II tracing, against routine maternal oxygen for category II or III tracings when the mother is not hypoxic, and expedited delivery for a category III tracing that does not respond to initial resuscitation. The summary page lists the recommendations; the guideline’s full text was not accessible when this article was written.
Interpretation is not perfectly consistent
A 2023 systematic review of 49 reliability studies found higher agreement for basic features of the tracing than for overall classification, higher agreement within the same observer than between observers, and great variation overall, which the authors said implies intrapartum cardiotocography should be used with caution in clinical decision making. They noted few high-quality studies. This does not make monitoring useless; it explains why clinicians use context, other findings and team discussion.

What this means for doulas
- Do not interpret tracings. Your role is to support the person, not to judge the screen.
- Do not predict. Avoid statements like “that looks fine” or “that is concerning.”
- Help the client ask. Questions such as “What are you seeing?”, “What does it mean for our plan?” and “What are our options?” are appropriate.
- Know what you can offer. Comfort measures within the clinical team’s guidance, calm presence and help with communication.
- Respect urgency. When the team is responding to a concerning tracing, step back and let them work.
Putting the evidence into practice
- In prenatal visits, explain in plain language that monitoring records heart rate and contractions, that it is common, and that your client can ask what the hospital’s routine is.
- Encourage clients to discuss monitoring preferences with their clinician before labor, recognizing that risk factors may change what is recommended.
- Prepare a few neutral phrases to use in the room, and practice them with your mentor.
- If the client is anxious about the sound or screen, offer breathing, touch and attention to the client rather than interpretation of the monitor.
- After a birth with a monitoring-related decision, listen to the family’s experience and refer questions about the decision to their clinician.
The bottom line
Electronic fetal monitoring is widespread, imperfectly reliable and associated with trade-offs, and its interpretation belongs to the clinical team. A doula who understands the basics can help families ask informed questions and stay supported, without reading the screen or giving an opinion on it.
Related reading: Understanding Hospital Policies: What Birth Doulas Should Know Before Attending a Birth; Understanding Common Obstetric Interventions and the Evidence Behind Them; The Difference Between Advocacy and Clinical Decision-Making in Doula Care.
This article is for professional education. It is not medical, legal, financial or tax advice. Check the standards of your certifying organization and the rules where you work.
Sources and further reading
- Alfirevic Z, et al. Continuous cardiotocography (CTG) as a form of electronic fetal monitoring (EFM) for fetal assessment during labour. Cochrane Database of Systematic Reviews 2017. Read the source
- American College of Obstetricians and Gynecologists. Committee Opinion No. 766 Summary: Approaches to Limit Intervention During Labor and Birth. Obstetrics & Gynecology 2019. Read the source
- Macones GA, et al. The 2008 National Institute of Child Health and Human Development workshop report on electronic fetal monitoring. Obstetrics & Gynecology 2008. Read the source
- American College of Obstetricians and Gynecologists. Clinical Practice Guideline No. 10: Intrapartum Fetal Heart Rate Monitoring: Interpretation and Management. Obstetrics & Gynecology 146(4), October 2025. Read the source
- Guideline Central. ACOG Intrapartum Fetal Heart Rate Monitoring: Interpretation and Management Guideline Summary (page read October 2026). Read the source
- Hernandez Engelhart C, et al. Reliability and agreement in intrapartum fetal heart rate monitoring interpretation: a systematic review. Acta Obstetricia et Gynecologica Scandinavica 2023. Read the source
Understanding monitoring well enough to support questions, and no further, is part of birth doula preparation. Birth & Baby University’s birth doula training and mentorship are outlined on the For Doulas page. Confirm how any program frames scope around clinical tools.
More for professionals: the Professionals Blog.


Leave a Reply